



Stack Details
The Ultima Muscle Mass SARMs stack is an elite-level protocol that combines four of the most powerful growth-promoting research chemicals available.
What’s Included
Some will call this stack overkill. For users who have already exhausted milder stacks and single-compound cycles, it represents a viable next step toward truly elite-level mass gains. To balance intensity with recovery, this stack also includes a FREE PCT component, ensuring users are equipped to properly recover after an aggressive cycle.
The Ultima Muscle Mass SARMs Stack includes:
- NEO SARMs Ibutamoren (MK-677) — 10 mg / 50 tablets ×1
- NEO SARMs Myostine (YK-11) — 10 mg / 50 tablets ×1
- NEO SARMs LigaMax (LGD-3033) — 10 mg / 50 tablets ×1
- NEO SARMs Testolone (RAD-140) — 10 mg / 50 tablets ×1
- Novo-Pharm Nolvadex (Tamoxifen Citrate) — 20 mg / 30 tablets ×1
Why This Stack Delivers “Ultimate” Mass
Each compound in this stack targets a different growth pathway, so you get no redundancy and a maximized total anabolic output.
MK-677 (Ibutamoren)
MK-677 is included to elevate growth hormone and IGF-1 levels, creating a hormonal environment that supports recovery, sleep quality, appetite, and long-term tissue growth. In this stack, it acts as the foundation that sustains training intensity and supports the massive anabolic load imposed by the other compounds.
YK-11 (Myostine)
YK-11 is used for its role in modulating the myostatin pathway, which normally limits muscle growth. By reducing this natural braking mechanism, YK-11 allows the anabolic signals from LGD-3033 and RAD-140 to translate into greater hypertrophy and muscle density.
LGD-3033 (LigaMax)
LGD-3033 provides a highly potent anabolic stimulus with a focus on strength and dense muscle gains. Its inclusion increases body weight that’s driven by contractile tissue rather than empty mass, reinforcing the “quality over volume” philosophy of this stack.
RAD-140 (Testolone)
RAD-140 serves as the primary androgen receptor driver in the stack. It delivers aggressive strength increases and muscle hypertrophy, allowing heavier training loads and faster progression on compound lifts, which directly fuels rapid mass accumulation.
Nolvadex (Tamoxifen Citrate)
Nolvadex is included as a critical recovery component, addressing the inevitable hormonal suppression caused by this level of anabolic signaling. Its role is to support post-cycle recovery and help preserve the gains achieved during the cycle.
Stack Recommendations
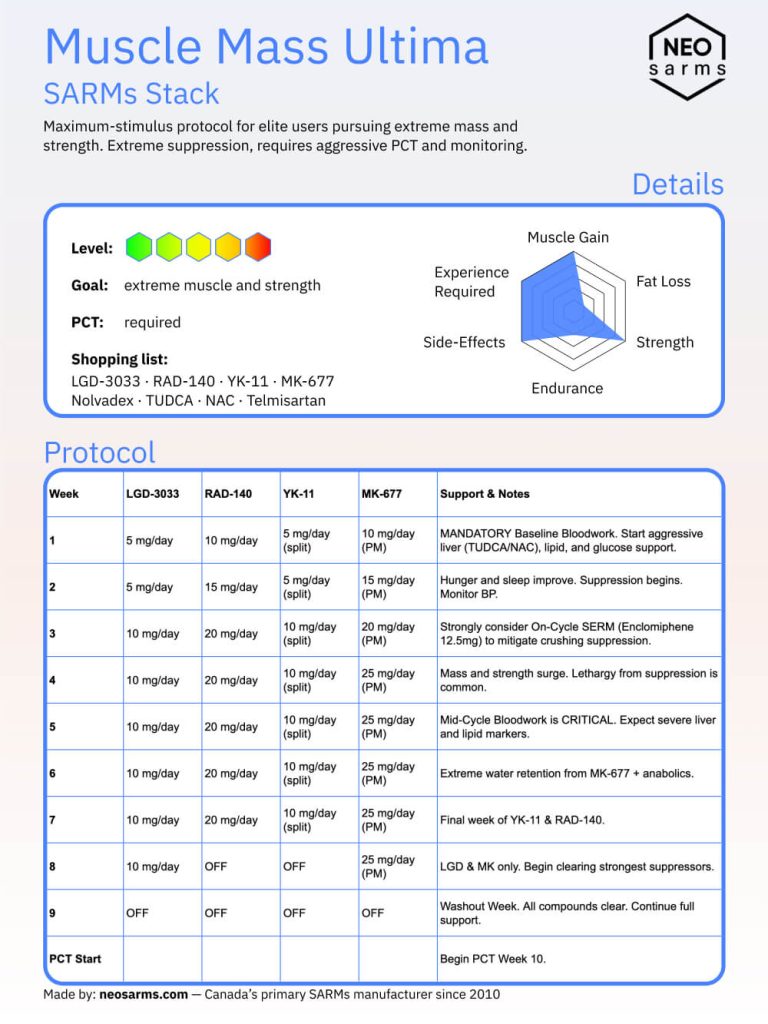
| Week | LGD-3033 | RAD-140 | MK-2866 | MK-677 | Support & Notes |
|---|---|---|---|---|---|
| 1 | 5 mg/day | 10 mg/day | 10 mg/day | 10 mg/day (PM) | Baseline Bloodwork. Start liver (TUDCA/NAC), lipid, and glucose (Berberine) support. |
| 2 | 5 mg/day | 15 mg/day | 15 mg/day | 15 mg/day (PM) | Hunger and sleep improve. Early strength gains from RAD. |
| 3 | 10 mg/day | 20 mg/day | 20 mg/day | 20 mg/day (PM) | Introduce Enclomiphene 12.5mg/day to combat suppression. Mass gains accelerate. |
| 4 | 10 mg/day | 20 mg/day | 20 mg/day | 25 mg/day (PM) | Significant water retention from LGD+MK-677. Strength is high. |
| 5 | 10 mg/day | 20 mg/day | 20 mg/day | 25 mg/day (PM) | Mid-Cycle Bloodwork is Critical. Expect liver and lipid stress. Monitor glucose closely. |
| 6 | 10 mg/day | 20 mg/day | 20 mg/day | 25 mg/day (PM) | Full anabolic effect. Joints feel supported despite heavy loads. |
| 7 | 10 mg/day | 20 mg/day | 20 mg/day | 25 mg/day (PM) | Final week of RAD-140 (most hepatotoxic). Continue others. |
| 8 | 10 mg/day | OFF | 20 mg/day | 25 mg/day (PM) | LGD, MK-2866, MK-677 continue. RAD clears. |
| 9 | OFF | OFF | OFF | OFF | Washout Week. All compounds clear. Continue full support. |
| PCT Start | — | — | — | — | Begin PCT Week 10 (See FAQ). |
This stack applies a “shotgun” approach: multiple pathways (androgen receptor agonism, myostatin inhibition, and GH/IGF-1 elevation) simultaneously. The physiological stress is notable with a mix like that, and a comprehensive, aggressive PCT is absolutely mandatory.
Bloodwork is the Bare Minimum
This demands pre, mid (week 5), and post (6-8 weeks after PCT) comprehensive panels:
- Full Liver
- Full Lipids
- Hormone Panel (Test, LH, FSH, Estro, Prolactin)
- Fasting Glucose & HbA1c
In addition, consider detailed IGF-1 levels analysis.
On-Cycle Support is Non-Negotiable
For liver, you need: TUDCA (500mg 2x/day) + NAC (1200mg/day).
- Lipids: High-dose EPA/DHA, Citrus Bergamot, Kyolic Garlic.
- Glucose: Berberine (500mg 3x/day with meals) is mandatory on MK-677.
- Blood Pressure: Hawthorne Berry, Celery Seed Extract. Monitor daily.
Also, Telmisartan may be considered for BP and cardiac protection.
Diet & Training
This stack requires a significant caloric surplus (+750-1000 kcal). Protein intake must be extreme (1.5g+/lb). Training should focus on heavy compound lifts with adequate recovery—the drugs build muscle, training triggers it. Overtraining is a high risk.
On-Cycle Therapy (OCT)
A SERM like Enclomiphene (12.5-25mg/day) from week 3 onward is highly advised to keep the HPTA partially active. This may prevent a total shutdown and make PCT marginally less difficult.
Have Emergency Measures
Have Aromatase Inhibitors (AIs) on hand in case of estrogenic sides from revived testosterone, and have your PCT and all supports ready before day one.




Eric S. –
Wild